October 24, 2026 | by Carezone Healthcare

Last Regulatory Review: 15 October 2026
Regulatory Context: Supreme Court of India • Department of Pharmaceuticals • NPPA • DPCO 2013
Current Court Matter: Kishan Chand Jain v. Ethics and Medical Registration Board & Ors.
Next Listed Hearing: 27 October 2026
Primary Audience: Patients, pharmaceutical companies, manufacturers, PCD franchise partners, distributors, wholesalers, retailers and healthcare-business professionals
India’s medicine price control framework in 2026 is under unusually intense scrutiny after two major developments arrived within days of each other.
First, on 8 October 2026, the Government of India approved a new 30% trade-margin cap for covered non-scheduled anti-cancer medicines. The Government says the measure could reduce prices of affected medicines by up to 70% and save cancer patients around ₹2,500 crore every year. A Directorate General of Health Services expert committee is to finalise the medicines that will be covered.
Then, during proceedings on 12 October 2026, the Supreme Court questioned why scrutiny of steep trade margins should stop at cancer drugs when concerns have also been raised about other medicines and medical consumables. The case is listed again for 27 October 2026.
This creates an important regulatory question for India’s pharmaceutical industry:
Could medicine price control eventually become broader than the present scheduled-drug framework and the newly approved cancer-drug margin cap?
The answer, as of 15 October 2026, is:
Possibly—but no universal new margin cap has yet been ordered for all medicines.
That distinction matters.
India already has a detailed drug-pricing framework under the Drugs (Prices Control) Order, 2013 — DPCO 2013, implemented principally through the National Pharmaceutical Pricing Authority — NPPA.
Scheduled medicines, non-scheduled medicines and certain new drugs are treated differently.
The new cancer-drug decision adds another layer: trade-margin rationalisation for selected non-scheduled anti-cancer medicines.
This Carezone Healthcare guide explains:
Two developments need to be understood together.
The Department of Pharmaceuticals announced that the Government had approved a cap on margins charged in the supply and sale of non-scheduled anti-cancer drugs.
Those margins are to be limited to 30% of the Maximum Retail Price.
The Government stated that:
Official Government announcement on the 30% cancer-drug margin cap
The Supreme Court subsequently questioned why the new approach should remain confined to cancer medicines when price differences and trade margins have also been raised in relation to other drugs and medical consumables.
The formal 12 October court record confirms that the matter was heard by a Bench comprising Justice Vikram Nath and Justice Sandeep Mehta and was listed again for 27 October 2026 at 2:00 PM.
India has approved a major new price-protection measure for selected non-scheduled anti-cancer medicines, while the Supreme Court is examining whether broader medicine and medical-consumable pricing issues also need attention.
The second part remains an ongoing judicial and policy question, not a completed nationwide price-control reform.
The Government’s 8 October 2026 announcement concerns non-scheduled anti-cancer medicines that will fall within the final approved list.
For those medicines, margins charged in their supply and sale are to be restricted to 30% of MRP.
Cancer treatment can involve:
The policy is therefore designed to reduce the gap between upstream medicine pricing and the amount eventually paid by patients.
Not necessarily.
There are different ways Government price intervention can operate.
A ceiling price directly limits the maximum permissible price of a scheduled formulation under DPCO.
A trade-margin rationalisation measure instead controls the margin available within the supply chain for covered products.
The policy objective may be similar—affordability—but the regulatory mechanism is different.
No—not on the basis of the 8 October announcement alone.
The Government has said an expert committee under the Directorate General of Health Services will finalise the medicines to which the new measure applies.
That means businesses should not assume:
“Every oncology medicine in India is now automatically under the new 30% cap.”
Many essential anti-cancer medicines are already included within the scheduled price-control framework.
In February 2026, the Government stated that NPPA had fixed ceiling prices for 131 scheduled anti-cancer formulations listed within Schedule I of DPCO 2013.
The new October measure targets the non-scheduled part of the oncology market.
Scheduled anti-cancer medicine
→ existing NPPA ceiling-price mechanism.
Covered non-scheduled anti-cancer medicine
→ new 30% trade-margin rationalisation framework once implementation/listing is completed.
Other non-scheduled medicine
→ existing DPCO rules continue unless another intervention applies.
The current litigation has highlighted substantial differences between the price at which certain medicines reach the trade and the MRP shown to patients.
During an earlier September hearing, the Supreme Court was told of a cancer medicine with a reported PTR of approximately ₹2,700 and an MRP of approximately ₹27,000.
The Bench reacted strongly to that reported disparity.
This example should be interpreted carefully.
It does not establish that:
It is a specific example raised in ongoing litigation and has become a catalyst for examining the broader system.
After the Government informed the Court about the 30% cancer-drug measure, the Bench questioned why the problem should be treated only within oncology.
Reports from the hearing indicate concern about significant markups across:
As of 15 October 2026, the Court has not issued a final universal order fixing a 30%, 16% or any other single margin for every medicine in India.
That broader issue remains open.
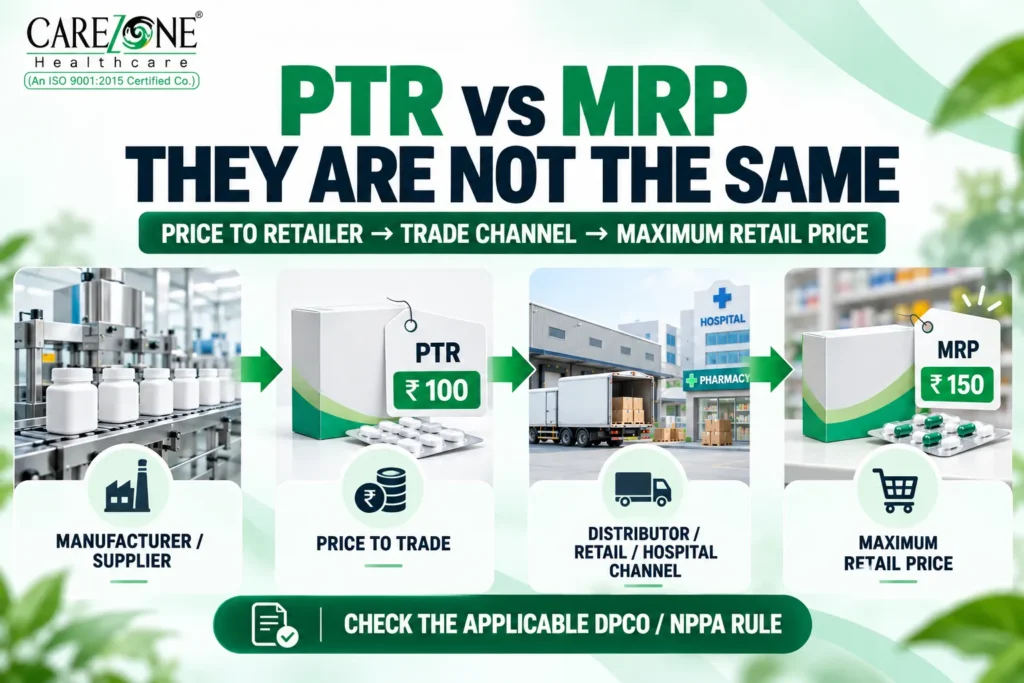
Understanding medicine price control requires understanding the pricing chain.
DPCO defines Price to Retailer as the price at which a drug is sold to a retailer, subject to the detailed statutory definition.
MRP is the maximum retail price displayed on the product pack.
The Government states that DPCO requires manufacturers to print the MRP on formulation labels and that a consumer should not be charged above the applicable current price-list price or labelled price, whichever is lower.
The difference may include parts of the commercial distribution chain such as:
The actual structure differs by product and channel.
No.
A difference between PTR and MRP should not automatically be labelled illegal merely because it is large.
The correct question is:
Does the pricing comply with applicable DPCO, NPPA, trade-margin and consumer-pricing requirements?
The current Supreme Court proceedings are examining whether the existing legal framework allows some price gaps to become unreasonably large even when the traditional annual MRP-increase rule is technically followed.
The Government has said that margins in the supply and sale of covered non-scheduled anti-cancer medicines will be limited to 30% of MRP.
That wording is important.
PTR + 30% = MRP
Trade-margin calculations depend on the precise regulatory methodology and pricing base adopted in the implementation framework.
For example, NPPA’s earlier 2019 anti-cancer trade-margin rationalisation used a defined pricing formula based on the relevant supply-chain price and the permitted trade margin.
Therefore manufacturers, marketers and distributors should not invent their own formula from newspaper headlines.
They should wait for and follow:
India does not apply one identical price-control mechanism to every medicine.
The central framework operates mainly through:
National Pharmaceutical Pricing Policy 2012
↓
Drugs (Prices Control) Order 2013
↓
National Pharmaceutical Pricing Authority
↓
Scheduled / Non-Scheduled / New Drug Pricing Rules
The Department of Pharmaceuticals confirms that NPPA regulates medicine prices under DPCO 2013.
Official Department of Pharmaceuticals DPCO 2013 page
Scheduled formulations are products covered by Schedule I of DPCO 2013, which is linked to India’s National List of Essential Medicines framework.
For these medicines, NPPA fixes a ceiling price.
Manufacturers, marketers and importers must sell the scheduled formulation within the applicable ceiling price, plus permissible taxes where applicable.
Government data stated that:
Manufacturers may sell different brands at different prices provided applicable pricing remains within the relevant ceiling-price requirements.
The Government has clarified that manufacturers can have different prices for the same scheduled formulation under different brand names as long as the prices remain below the NPPA ceiling.
A non-scheduled formulation is a formulation that does not fall within the relevant Schedule I pricing category under DPCO.
The legal definition is contained in DPCO 2013.
No.
This is one of the biggest misunderstandings surrounding medicine pricing.
For non-scheduled formulations, manufacturers generally have greater freedom in setting prices.
However, they cannot increase the MRP by more than 10% of the previous MRP during the preceding 12 months.
NPPA also monitors prices and has powers under DPCO to intervene in extraordinary circumstances and in the public interest.
Non-scheduled does not mean “no price regulation.” It means the medicine is not subject to the same routine ceiling-price mechanism as a scheduled formulation.

For a non-scheduled formulation, the manufacturer is required not to increase its MRP by more than 10% during the preceding 12 months.
Suppose the MRP of a non-scheduled formulation is:
₹100
A manufacturer cannot simply revise that MRP to:
₹125
within the applicable 12-month period under the normal 10% rule.
The permitted increase is capped by the DPCO framework.
No.
Ten percent is a maximum permissible annual increase, not a mandatory annual increase.
A manufacturer can:
Government data from June 2026 indicated that the weighted average annual price increase in non-scheduled drugs over the previous three years was 6.94%, below the permissible maximum.
This is one of the most important issues in the current Supreme Court debate.
The annual 10% rule principally controls subsequent MRP increases of non-scheduled formulations.
It is different from imposing a universal ceiling on the initial market price of every non-scheduled drug.
That distinction is one reason the current litigation has focused attention on whether a product could enter the market with a large PTR–MRP gap and then technically remain within the annual 10% increase limit.
The 10% rule restricts annual MRP increases for non-scheduled formulations; it is not the same thing as a universal upfront price ceiling for every non-scheduled medicine.
This is why:
annual price control
and
initial price / trade-margin control
should not be treated as identical regulatory concepts.
The National Pharmaceutical Pricing Authority is the central pharmaceutical-pricing regulator under the Department of Pharmaceuticals.
Its functions include:
Official NPPA information on medicine pricing and price-control interventions
DPCO also provides powers allowing price intervention in extraordinary circumstances and the public interest.
Government releases continue to reference Para 19 of DPCO 2013 as an important intervention mechanism.
DPCO stands for:
Drugs (Prices Control) Order, 2013.
It is India’s central medicine-price-control framework issued under the Essential Commodities legal structure.
DPCO covers areas including:
A PCD pharma company or marketer may deal with hundreds of products.
Some may be:
One pricing assumption should therefore not be applied automatically to the entire product catalogue.
Yes.
For a scheduled formulation, the ceiling price is the upper regulated limit rather than a mandatory selling price.
DPCO expressly provides for a scheduled formulation to be priced at or below the applicable ceiling price.
A company may choose a lower commercial price.
However, all applicable:
requirements still need to be followed.
No.
MRP means Maximum Retail Price.
Government guidance states that no person should sell a formulation to a consumer above the applicable current price-list price or the price shown on the container/pack, whichever is lower.
This distinction is crucial.
Ceiling Price
= regulatory maximum applied to scheduled formulation pricing.
MRP
= maximum retail amount displayed to the consumer.
PTR
= price at which the product is sold to a retailer under the applicable pricing definition.
Trade Margin
= commercial margin within the distribution/sale chain, calculated according to the relevant regulatory framework.
Cancer treatment presents a particularly strong affordability concern because:
The Government has therefore already used price-control interventions extensively in oncology.
As of early 2026, NPPA had fixed ceiling prices for 131 scheduled anti-cancer formulations.
The October decision now seeks to extend stronger price protection into part of the non-scheduled oncology market.
The concept of anti-cancer trade-margin rationalisation is not completely new.
In February 2019, NPPA initiated a trade-margin rationalisation pilot covering 42 non-scheduled anti-cancer medicines.
NPPA says the intervention generated savings of up to 90% across 526 brands, amounting to approximately ₹984 crore annually.
The 2026 policy can be understood partly as an expansion of a mechanism India has already used.
It demonstrates that Government can pursue affordability through more than one route:
Schedule-I ceiling pricing
or
special trade-margin rationalisation
or
public-interest intervention.
Possibly—but that has not yet happened universally.
This is where Carezone’s article must remain precise.
The Supreme Court questioned the Government about price disparities beyond cancer medicines on 12 October.
That means the broader policy issue is clearly under judicial scrutiny.
However:
Court questions ≠ final nationwide rule.
As of 15 October 2026:
Future policy discussions could potentially examine:
These are possible policy directions, not confirmed rules.

Medical-device pricing is also part of the wider affordability debate.
India has previously used price-control measures for products such as:
NPPA itself notes that trade-margin caps have previously been used for devices as an affordability intervention.
During the October 2026 Supreme Court proceedings, concerns were also raised regarding markups on medical devices and consumables.
This does not mean every medical consumable has already received a new 2026 price cap.
It means the broader issue is being examined.
The immediate impact depends on whether a company’s products are covered by:
Determine whether the formulation is:
Check the existing MRP and previous price-change date.
For non-scheduled formulations, verify compliance with the 10% preceding-12-month rule.
Review:
Do not rely on old price files.
NPPA and Government notifications can create new obligations for particular categories.
Third-party brand owners often focus on:
manufacturing rate + packaging + MOQ + MRP + market margin.
But medicine pricing cannot be decided only through a sales calculation.
Before approving commercial artwork, the brand owner should ask:
Carezone Healthcare supports third-party manufacturing discussions across multiple pharma, nutraceutical and cosmetic categories, subject to formulation feasibility, packaging, documentation and applicable regulatory requirements.
Explore Carezone Healthcare Third-Party Manufacturing
Manufacturing cost does not by itself determine a legally compliant medicine MRP.
Pricing must be checked against the applicable regulatory classification.
PCD companies and franchise partners work directly with:
That makes medicine-price regulation commercially important.
Mistake 1: Assuming every product has the same margin structure.
Mistake 2: Assuming non-scheduled means completely unregulated.
Mistake 3: Using an old MRP after a regulatory price revision.
Carezone Healthcare’s PCD franchise platform supports business discussions across multiple product categories and therapeutic segments.
Explore Carezone Healthcare PCD Franchise Opportunities
Carezone’s earlier Indian pharma market analysis explains how market value can be affected by:
That distinction is also relevant when interpreting industry growth alongside tighter medicine-price regulation.
Read Carezone’s Indian Pharma Market 2026 analysis
A distributor should not look only at:
purchase price vs selling price.
Compliance also requires awareness of:
MRP is a maximum—not a compulsory selling price.
A retailer may sell below MRP.
But selling above the lawful applicable maximum can raise overcharging concerns.
A very low medicine price does not automatically mean a product is counterfeit.
Likewise, a high MRP does not automatically prove the product is fake.
Authenticity requires separate checks involving:
Carezone recently examined this problem in the context of counterfeit high-value cancer medicines.
Read Carezone’s Counterfeit Cancer Drugs India 2026 guide
Pricing and promotion are separate compliance areas, but they interact.
For example:
Carezone’s recent Pharma Marketing Rules India 2026 guide explains the current Supreme Court review of UCPMP, gifts, samples, CME and pharmaceutical marketing practices.
Read Carezone’s Pharma Marketing Rules India 2026 guide
The combined principle is:
Compliant product + compliant pricing + compliant promotion + traceable distribution.

| Compliance Question | What to Verify |
|---|---|
| Product classification | Scheduled, non-scheduled or DPCO-defined new drug |
| Schedule I | Whether the formulation is within the applicable scheduled list |
| Ceiling price | Latest NPPA ceiling notification |
| Retail price | Whether NPPA has fixed a product-specific retail price |
| Existing MRP | Current approved/declared MRP |
| Previous MRP | Price during preceding 12 months |
| 10% rule | Whether a non-scheduled MRP increase remains within limit |
| Special intervention | Any Para 19 / trade-margin / category-specific order |
| Trade chain | PTS/PTR/distributor/retailer structure as applicable |
| Price list | Whether the current price list reflects the lawful price |
| Packaging | Correct MRP printed on pack |
| Batch transition | Treatment of existing vs revised-price stock where applicable |
| Distributor communication | Current price shared downstream |
| Invoice trail | Price and product traceability |
| Court / policy updates | New Government or NPPA decisions monitored |
Three things are now worth monitoring.
The Government has said the DGHS expert committee will finalise which non-scheduled anti-cancer medicines will be covered by the new trade-margin cap.
Until that process is completed, businesses should avoid presenting an unofficial media list as the final statutory list.
The industry will need clarity regarding:
The Supreme Court’s formal 12 October order lists the connected matters for 27 October 2026 at 2:00 PM.
The major question is whether the Court and Government discussion will remain focused on:
anti-cancer medicines
or expand further toward:
other non-patented medicines + devices + consumables.
Any such expansion should be reported only after an official order or policy decision.

India’s medicine price control framework in 2026 is entering an important new phase, but the current changes should not be overstated.
The Government has approved a 30% trade-margin limit for covered non-scheduled anti-cancer medicines.
The final covered-drug list is to be determined through a DGHS expert committee.
The Government estimates that the intervention could reduce prices of affected medicines by up to 70% and save patients around ₹2,500 crore each year.
At the same time, the Supreme Court is asking a wider question:
Why should unusually large medicine and medical-consumable markups be examined only in cancer treatment?
That wider question is important—but it is not yet a universal new price-control rule.
For now, pharmaceutical businesses should continue to distinguish clearly between:
Scheduled formulations
→ NPPA ceiling-price control.
Applicable new drugs
→ NPPA retail-price fixation.
Non-scheduled formulations
→ greater initial pricing flexibility but a maximum 10% MRP increase during the preceding 12 months, subject to other applicable interventions.
Covered non-scheduled anti-cancer products
→ upcoming/expanded 30% trade-margin rationalisation framework.
Special categories / public-interest cases
→ additional NPPA intervention may apply.
For manufacturers, marketers, PCD partners and distributors, the safest commercial principle is:
Never set, revise or communicate a medicine price before checking its exact regulatory category and the latest applicable NPPA/Government order.
India regulates medicine prices primarily through DPCO 2013 and NPPA. Scheduled formulations have Government-fixed ceiling prices, certain new drugs receive NPPA retail prices, and non-scheduled formulations are subject to rules including the maximum 10% MRP increase over the preceding 12 months.
The Government approved a measure on 8 October 2026 limiting margins in the supply and sale of covered non-scheduled anti-cancer medicines to 30% of MRP. A DGHS expert committee is to finalise the covered medicines.
No. Scheduled anti-cancer formulations may already have NPPA ceiling prices, while the new trade-margin measure concerns non-scheduled cancer medicines selected under the new framework.
The Government says the measure could reduce affected medicine prices by up to 70%. That does not mean every covered cancer medicine will automatically become exactly 70% cheaper.
PTR generally means Price to Retailer—the price at which a drug is sold to a retailer under the DPCO pricing definition.
MRP means Maximum Retail Price. It is the maximum retail price shown on the product pack. A consumer should not be charged above the lawful applicable maximum.
PTR is an upstream trade price, whereas MRP is the maximum price to the final consumer. The difference can contain trade margins and other permitted commercial components depending on the supply chain.
A scheduled formulation is a formulation covered under Schedule I of DPCO. NPPA fixes ceiling prices for such medicines.
A non-scheduled formulation is outside the applicable Schedule-I ceiling-price list. Its MRP is not controlled through the same routine ceiling-price mechanism, but its pricing is still subject to DPCO requirements.
A manufacturer cannot increase the MRP of a non-scheduled formulation by more than 10% of the MRP during the preceding 12 months under the normal DPCO rule.
No. Ten percent is a maximum permissible increase for applicable non-scheduled formulations, not a compulsory price increase.
Yes. A ceiling price sets the upper regulatory limit. A manufacturer can sell below that limit.
No. MRP is the maximum retail price. Applicable DPCO and consumer-pricing requirements prohibit charging beyond the lawful maximum.
No. As of 15 October 2026, the Court has questioned the wider pricing structure but has not imposed one universal trade-margin cap on every medicine.
The formal 12 October court order lists the matter for 27 October 2026 at 2:00 PM.
Medicine pricing is one part of responsible pharmaceutical business.
Commercial planning should also account for:
Carezone Healthcare, Ambala, supports business discussions across pharmaceutical, nutraceutical and selected cosmetic categories.
Carezone’s current product catalogue spans multiple dosage forms and therapeutic categories for business enquiry and product discussion.
Explore Carezone Healthcare Product Range
Explore Carezone Healthcare PCD Franchise
Discuss Third-Party Manufacturing with Carezone Healthcare
Contact Carezone Healthcare for Business Enquiries
Product availability, MRP, packing, licensing, documentation, manufacturing feasibility and commercial terms should always be confirmed for the specific product and applicable regulatory position.
This article is intended for general educational, pharmaceutical-business and regulatory awareness only.
It is not:
Medicine-pricing obligations can vary depending on:
Pharmaceutical companies and businesses should verify the latest Department of Pharmaceuticals / NPPA documents and obtain appropriate regulatory or legal advice before implementing a material pricing change.
Because the Supreme Court proceedings and the new cancer-drug policy implementation are ongoing, this article should be reviewed again after the 27 October 2026 hearing and after publication of the final covered anti-cancer medicine list.
View all




